


Reviewed by Dr Nico Kamosi, last updated October 2026.

At a glance
- Material: Metal-free zirconia.
- System: NobelPearl or Z-system two-piece ceramic dental implants.
- Fees: Placement from £2,000 and the ceramic implant crown from £1,750.
- Location: Knightsbridge, London.
Zirconia Ceramic or Titanium Implants: when to choose which?
The majority of dental implants are made of titanium. Following years of scientific research and development, ceramic implants have become an increasingly popular alternative. Titanium implants have also been advocated and used for more than 5 decades for a variety of clinical indications in oral restorative rehabilitation.
Zirconia white dental implants, a new generation of white ceramic dental implants, offer high material density, hardness, tensile strength and modulus of elasticity.
Every patient case is unique in terms of clinical and biological presentation. Therefore, each case should be assessed and planned meticulously to justify the indications for the use of titanium versus ceramic implants.
Dr. Nico Kamosi

Dr. Nico Kamosi
Specialist periodontist, with postgraduate master’s training and experience in implant dentistry and prosthodontics; holistic and biological dentist.
TDL. DDS. (Swe.), MSc.Perio.(Eng.),
MClinDent.Perio.(Eng.), MSc.Imp.Dent.(Eng.),
Dip.Aesth.Med. (Eng.), MClinDent.Prosth.(Eng.),
Cert., Dip.DHSLM.(RCS.Eng.), Cert.Orth.(Eng.), Cert.Law (Eng.), AIAOMT
Accredited member of IAOMT, SMART Certified
Member of AACD, EFP, AAP, ESCI, IAOMT
Dr Nico’s ceramic implant experience
I have been placing ceramic, particularly zirconia, dental implants for a few years. I initially started working with the NobelPearl two-piece zirconia implant system and subsequently incorporated the Z-System two-piece zirconia implant system into my clinical treatment options. Over the years, I have placed a good number of ceramic implants, although the number varies from year to year depending on patient demand and individual treatment requirements.
My philosophy is that there is no single implant material that is ideal for every patient. Ceramic implants can be an excellent option for appropriately selected patients, particularly those who want a metal-free restoration and have suitable bone, occlusion, functional loading and restorative requirements. However, the priority should always be the patient’s long-term biological health, function and predictability, rather than simply choosing a particular material.
Comparing ceramic and titanium implants
Ceramic and titanium implants differ in material, system design, research history and cost.
| Feature | Zirconia ceramic implants | Titanium implants |
|---|---|---|
| Material | Metal-free ceramic | Titanium metal |
| Appearance through thin gum | Ivory-coloured material that does not show through in the same way as titanium | May show through thin gum |
| Research described on this page | More than 15 years of research for NobelPearl | Research and clinical use dating back to the 1960s |
| System options | One-piece systems and two-piece systems, including screw-retained NobelPearl | Systems for single restorations and complex total rehabilitation |
| Implant placement | From £2,000 | From £1,500 |
Final costs are confirmed after examination and supplied in a written estimate. See our dental fees.
Read our comparison of ceramic and titanium implants.
Titanium implants – Benefits and challenges
Since the 1960s, titanium implants have been dominating the world of dental implantology. Therefore, it goes without saying that the scientific and clinical research on dental implantology is mainly based on the development and performance of titanium implant systems.
As a result, clinicians and patients considering the implementation of ceramic implants (specifically, zirconia) to support all types of fixed and removable prostheses require comprehensive research.
With regard to opting for an appropriate implant material, one needs to know the indications and shortcomings of both types of dental implants.
Benefits of Titanium implants
Scientific evidence: There is a wealth of scientific evidence since Prof P-I Brånemark discovered the phenomenon of natural bone attachment to titanium–osseointegration over 65 years ago.
The versatility, bio-mechanical stability and satisfactory user experiences have gained high levels of trust regarding the performance of pioneer titanium implant systems.
A variety of indications: Titanium implant systems offer solutions for most clinical situations, e.g., single restorations or complex total rehabilitation cases.
Mechanical Strength: Titanium is highly resistant to high external forces. Hence, there is seldom any report of implant fractures.


Challenges of Titanium implants
Although hypersensitivity and allergic reactions to titanium have been reported to be rare, as low as just 0.6% among patients, this specific category of patients would benefit from metal-free ceramic implants. Therefore, metal allergy or hypersensitivity could be considered one of the drawbacks of titanium implants.
We advise and refer patients for a metal allergy test when they are concerned about being allergic to titanium metal.
Why choose ceramic implants over titanium implants?
The increasing demands on the use of metal-free, natural-looking dental materials and restorations, along with advances in material science, technology, and development, would be beneficial to our patients with highly aesthetic and strong natural ceramic implants.
They have excellent mechanical properties in flexural and tensile strength that are compatible with most clinical requirements without compromising aesthetics and functionality.
Zirconia ceramic implants – Benefits and challenges
Challenges with ceramic implants
- Fewer case studies are published to present all of the performed clinical indications for the use of ceramic implants as a solution for bridges and full-mouth rehabilitations. The case studies mainly present single tooth replacement and bridge cases.
- A limited number of clinicians performing ceramic implants
- The limited biomechanical strength and flexibility of the old-generation ceramic implants
- Lack of skills in both surgical and restorative aspects of ceramic implant dentistry
- Limitations in the design and architecture of the implants and their connective parts
- Most of the ceramic implants belong to the One-piece / Cement-retained systems.
- Due to both implants’ limited structural and mechanical flexibility and their connectors/ restoration, One-piece/ cement-retained Zirconia implant systems have fewer clinical indications than two-part screw-retained ones.
- The complex engineering and manufacturing process involved in the production of Zirconia implants renders them more costly.
- The complex laboratory and layering process involved in the production of Zirconia supra-structures, e.g. crowns, bridges, etc., renders them more costly.
Benefits of ceramic implants
The corrosion-resistant nature of the ceramic material and its low affinity to plaque result in a lower risk of inflammation.
Unlike titanium implants, these ivory-coloured natural ceramic implants would not shine through a thin gingival biotype.
The zirconium dioxide (Zirconia) peri-implant soft tissue seal, blood flow, and the orientation of the collagen fibres are comparable to periodontal soft tissue around the natural teeth.
The low plaque affinity and bacterial adhesion explain the presence of a lower level of plaque retention, hence reducing peri-implant inflammatory diseases and biological complications. Clinical research reveals that ceramic implants minimise surface plaque adhesion and accumulation, hence maintaining the surrounding peri-implant gum health.
Ceramic implants offer ultimate white, natural aesthetics while promoting natural surrounding gum, hence a natural appearance.
Ceramic implants provide flexibility and predictability throughout the restorative workflow, hence reducing the risk of long-term biomechanical failures.
Is zirconia metal-free?
During irreversible chemical reactions, the oxidation of zirconium, a non-metallic or metal-free ceramic zirconia, is created with improved wear resistance, toughness, and conductivity properties. Hence, ‘Zirconia’ is a ceramic material which is manufactured from zirconium dioxide.
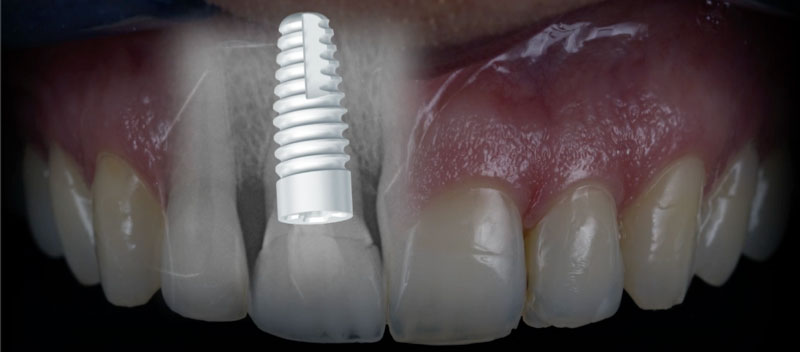
The Nobel-Biocare system, with pioneering scientific-proven premium quality and evidence-based clinical excellence, has been used by world experts since 1965. NobelPearl™ offers two-piece individual abutments, gingiva formers, and 100% Carbon-Ceramic technology designated for a strong, resilient, long-lasting implant-abutment screw-retained connection. NobelPearl™ Zirconia implants, with more than 15 years of evidence-based research, have reported a high rate of osseointegration and success comparable to titanium implants.
Who can have ceramic implants?
The first consideration is that the patient must be suitable for dental implant treatment in general. Before considering any implant, we assess the patient’s medical history, healing capacity, periodontal health, oral hygiene, bone availability, occlusion, functional loading and lifestyle factors.
Conditions that may affect suitability for implant surgery include certain uncontrolled systemic diseases, uncontrolled diabetes, significant bleeding disorders, some cardiovascular conditions, disorders affecting bone metabolism, significant immunological or medical compromise and other circumstances that may adversely affect surgical healing. These conditions do not necessarily mean that an implant is impossible, but they may require medical assessment, optimisation or modification of the treatment plan.
A patient should also have good oral hygiene and be sufficiently motivated to maintain the implant and surrounding tissues. Smoking and tobacco use can adversely affect periodontal and peri-implant health, and ideally patients should be non-smokers or should stop or substantially reduce smoking before and during treatment.
Clenching and Grinding
Patients with significant bruxism, clenching or other parafunctional activities require particularly careful assessment. This does not automatically exclude them from ceramic implant treatment, but the implant position, prosthetic design, occlusion and loading need to be carefully planned. In selected cases, a protective night guard may be recommended following treatment.
Available bone
There needs to be adequate bone height and width to accommodate the selected implant safely and predictably. Some zirconia implant systems have limitations regarding available implant lengths and prosthetic components. For example, where the available bone height is very limited, a short zirconia implant may not be an option.
In the posterior maxilla, insufficient bone height may therefore require sinus floor elevation and/or bone augmentation before an implant can be considered. Similarly, in the posterior mandible, the position of the inferior alveolar nerve is an important anatomical consideration.
Implant position and angulation
Three-dimensional implant positioning is particularly important with ceramic implant systems. Depending on the implant system, there can be more limited restorative flexibility compared with some titanium implant systems, particularly where complex angulation or customised abutment solutions are required. Patients with significant skeletal discrepancies, severe bone atrophy, unfavourable occlusion or complex restorative requirements may therefore require particularly careful planning, and in some cases titanium may offer greater restorative flexibility.
From consultation to your final crown
Treatment involves assessment, planning, implant placement, healing and restoration.
Stage 1: Consultation and assessment
The first stage involves a comprehensive clinical examination and assessment of:
- General and dental health
- Periodontal health
- Existing teeth and restorations
- Occlusion and bite
- Bone availability
- Functional and parafunctional activity
- Oral hygiene
- Medical history and relevant risk factors
- Patient expectations and preferences
Appropriate radiographic investigation is then undertaken. This may include intraoral radiographs, an OPG and/or CBCT imaging, depending on the clinical circumstances.
Stage 2: Treatment planning
Where required, we plan the implant position using digital imaging and guided implant planning. The objective is to achieve an implant position that provides appropriate bone support while also allowing an appropriate restorative outcome.
Where there is inadequate bone, additional procedures may be necessary.
These can include:
- Bone augmentation
- Ridge augmentation
- Socket preservation following extraction
- Sinus floor elevation
- Guided bone regeneration
In selected cases, augmentation and implant placement may be undertaken simultaneously. In other cases, a staged approach is safer and more predictable.
Read about guided bone regeneration and atraumatic tooth extraction.
Stage 3: Implant placement
The ceramic implant is placed according to the planned three-dimensional position. Where appropriate, guided implant surgery may be used to improve the accuracy of implant placement. The timing of loading and restoration depends on the individual clinical circumstances, implant stability, bone quality and quantity, the implant system used and whether additional regenerative procedures have been undertaken.
Stage 4: Healing period
Ceramic implants may require a longer healing period than some conventional titanium implant protocols, depending on the clinical situation. In my practice, I allow additional healing time where clinically appropriate rather than rushing the restorative stage. Where bone augmentation, extraction or sinus elevation has been undertaken, the overall treatment time may be considerably longer.
Stage 5: Impression and Restoration
Once the implant has healed adequately and both the clinical and radiographic assessments indicate that it is ready for restoration, we proceed with the restorative phase. Digital scanning or conventional impressions may be used, depending on the case, followed by the fabrication and fitting of the definitive ceramic restoration. The final restoration is designed to take account of the patient’s occlusion, aesthetics, function and long-term maintenance.
Ceramic implant costs
Ceramic implant placement and its definitive crown start from a combined £3,750, before any additional procedures.
| Treatment | Fee |
|---|---|
| Premium zirconia ceramic implant placement | From £2,000 |
| Premium ceramic zirconia implant crown | From £1,750 |
| Bone regenerative/augmentation procedure (GBR) | From £1,000 |
| Sinus augmentation | From £1,350 |
| Socket preservation | From £900 |
| Biological extraction | From £750 |
| CBCT scan | From £150 |
| CBCT report | From £100 |
| Premium titanium implant placement, for comparison | From £1,500 |
Your final cost will be confirmed after examination, with a written estimate. See our dental fees.
These fees are for the implant placement and restorative crown and do not include additional procedures that may be required.
The overall cost can increase where the patient requires procedures such as:
- Atraumatic tooth extraction
- Bone grafting
- Guided bone regeneration
- Ridge augmentation
- Sinus floor elevation
- Additional surgical procedures
- Temporary restorations
- More complex laboratory work
- Additional diagnostic or digital planning
Ceramic implant treatment can also be more expensive than conventional titanium implant treatment because of the cost of the implant components and the associated laboratory and restorative procedures. A precise quotation can therefore only be provided after clinical assessment and treatment planning.
Ceramic implant patient stories
These cases show how treatment was staged around each patient’s periodontal health, bone and restorative needs.
Rehabilitation with 9 ceramic implants
One of the most extensive cases involved a patient who required approximately 9 Nobel Pearl® ceramic implants as part of comprehensive rehabilitation. The patient presented with multiple failed or infected root canal-treated teeth, failed restorations, recurrent decay associated with existing bridgework and significant deterioration of the dentition.
The treatment was deliberately undertaken in stages. First, we addressed the active periodontal disease and stabilised the periodontal condition. We then progressively dealt with infected and non-restorable teeth using atraumatic extraction techniques where indicated, followed by appropriate bone grafting and ridge preservation or augmentation.
After allowing appropriate healing, ceramic implants were placed in the rehabilitated areas. The implant treatment was planned using guided surgery to help achieve accurate three-dimensional implant positioning and appropriate restorative relationships.
Importantly, I did not remove all of the patient’s teeth simply to facilitate the treatment. Wherever possible, we preserved and treated teeth that had a reasonable long-term prognosis.
The final rehabilitation incorporated ceramic crowns on natural teeth and ceramic implant-supported restorations. The treatment was completed progressively rather than all at once, allowing us to monitor the patient’s healing and periodontal stability at each stage. The patient has now been under ongoing follow-up for approximately two years, with the result remaining clinically stable to date.
This is one patient’s experience; results vary.
Replacing a denture that moved during speech
The patient relied on his voice for work and was concerned about his denture moving while he spoke.
Another patient had not attended a dentist for approximately 15 years and had been wearing a denture. He wanted a more stable, functional solution and specifically wished to avoid metal and have zirconia implants. He also had areas of infection and periodontal disease that needed to be addressed before implant treatment.
Following periodontal treatment, CBCT assessment and comprehensive treatment planning, we used guided implant surgery. Most of the implants could be placed during one surgical stage. One particularly compromised upper anterior site required a staged approach: the tooth was removed, the area was grafted and allowed to heal for approximately five to seven months before the additional implant was placed.
After the healing and restorative stages had been completed, the patient received 8 Z-System® zirconia implant-supported single crowns. The patient had relatively strong functional loading, so a night guard was provided as part of the long-term protective strategy.
The technical aspects of the treatment were important, but so was the patient relationship. He was extremely anxious at the beginning of treatment. By taking the treatment step by step, explaining each stage carefully and building mutual trust, we were able to complete a complex treatment successfully.
This describes one patient’s experience; results vary.
Dental implant case studies
See our dental implant before and after photos from our happy patients.
When titanium may be more suitable
I do not believe that ceramic implants are automatically better than titanium implants for every patient. Where there is no specific clinical or material-related reason to avoid titanium, titanium remains a highly established and versatile implant material, with extensive long-term clinical evidence and a wide range of restorative options.
I would be more inclined to recommend titanium where:
- The available bone is severely limited
- The implant requires a particularly short or specialised design that is not available in the selected ceramic system
- Complex implant angulation is required
- The prosthetic restoration requires greater restorative flexibility
- There is significant parafunctional loading
- The adjacent teeth are hyper-mobile
- The case requires complex or customised prosthetic components
- The anatomical or restorative circumstances make a ceramic implant less predictable
Conversely, where the patient strongly prefers a metal-free solution and the anatomical, biological and functional circumstances are compatible, a ceramic implant can be an excellent treatment option. In such case scenarios, the decision should therefore be patient-specific.
Longevity, complications and aftercare
In my clinical experience, appropriately selected and properly maintained ceramic implants can remain functional for many years. The implant itself is only one component of the treatment. The bone, soft tissues, implant connection and prosthetic restoration all need to remain healthy and stable.
As with all implant treatment, ceramic implants can have complications. In my experience, the complications I have encountered have included prosthetic screw loosening and, in isolated cases, screw fracture. These problems can be associated with excessive functional loading, strong biting forces, clenching or grinding and other parafunctional activity.
This is one reason why careful occlusal planning is particularly important. For patients who demonstrate significant clenching or grinding, I may recommend a protective night guard.
Regular professional reviews are also important. I prefer to identify and manage potential problems at an early stage rather than waiting until a complication becomes more advanced. For this reason, patients receiving implant treatment should remain within a structured long-term maintenance programme, including appropriate clinical and radiographic review where indicated.
Read more about implant complications and their management.
Visit our Knightsbridge clinic
The clinic is on Brompton Road in Knightsbridge.
Address: Unit A, 4th Floor, 193-195 Brompton Road, Knightsbridge, London SW3 1NE
Nearest Tube: Knightsbridge (Piccadilly line)
Phone: 020 7207 5222
Questions about ceramic implants
Suitability, material choice and cost depend on your assessment and treatment plan.
Zirconia ceramic dental implants are the best alternatives for titanium dental implants.
Our Specialists are registered with the General Dental Council and have been teaching advanced implantology and periodontology in England and abroad for a few years.
At London Specialist Dentists, our specialists implement the latest technology and innovations in the field of implant dentistry and offer the most scientifically proven ceramic implants.
Dr Nico Kamosi has developed high expertise and extensive experience in the fields of periodontology, implant dentistry, and full mouth rehabilitation on an advanced level for over 25 years.
MELISA stands for Memory Lymphocyte Immunostimulation Assay. It is an in-vitro blood-based laboratory test that assesses lymphocyte reactivity to selected metals and other substances. It is different from a conventional skin patch test and is sometimes considered when there is a clinical concern about possible metal hypersensitivity.
In my practice, I do not recommend MELISA testing routinely for every patient considering an implant. I would consider testing where there is a relevant history or clinical concern about metal hypersensitivity, particularly where the patient has previously experienced suspected reactions to metal-containing dental or medical materials or has a significant history that warrants further investigation.
Testing can also be considered where a patient has a strong preference to understand their individual reactivity to particular dental alloys before treatment. Depending on the clinical circumstances, the laboratory profile can be selected to investigate specific metals, which may include components found in dental alloys such as nickel, cobalt, chromium, molybdenum, copper or other metals.
Where testing is undertaken, the results need to be interpreted in the context of the patient’s clinical history. A laboratory result should not be regarded in isolation as a definitive prediction of whether a particular implant will succeed or fail.
I have treated a patient who was approximately 75 years old and had previously undergone MELISA testing. He reported that his previous test had indicated reactivity to Titanium and zirconia. Interestingly, he subsequently underwent zirconia implant treatment without experiencing an adverse clinical reaction, and the treatment progressed successfully.
Later, when he required further implants in the lower jaw, the anatomical circumstances were different. There was insufficient bone height above the inferior alveolar nerve to safely accommodate the available zirconia implant design, and 3 short titanium implants were considered a more appropriate option.
Because the patient had previously raised concerns regarding metal sensitivity, we decided to undertake further investigation rather than simply assuming that titanium was unsuitable. The subsequent MELISA testing did not demonstrate delayed lymphocyte hypersensitivity to the titanium tested. The patient subsequently received a titanium implant-supported bridge and has continued to function well without a clinically evident reaction.
This case demonstrates why I believe patient history, clinical examination, anatomy, material selection and laboratory investigations should all be considered together. A test such as MELISA can provide additional information in selected patients, but it should not be presented as an absolute predictor of implant compatibility or long-term implant success.
This is one patient’s experience; results may vary from case to case!
Learn about metal hypersensitivity testing.
Current clinical evidence indicates that modern zirconia implants can achieve high survival rates and can provide long-term function. However, it would not be responsible to promise a particular lifespan for an individual implant.
The longevity of an implant depends on many factors, including:
- Quality and quantity of bone
- Implant position
- Periodontal and peri-implant health
- Oral hygiene
- Occlusal loading
- Prosthetic design
- Smoking
- General health
- Parafunctional activity
- Regular professional maintenance
- Patient cooperation
- Limitations in the design and architecture of the implants and their connective parts
- Limited structural and mechanical flexibility of their connectors/ restoration, One-piece / Cement-retained Zirconia implant systems have fewer clinical indications than two-part screw-retained ones.
- The complex engineering and manufacturing process involved in the production of Zirconia implants and their restorative parts renders them more costly.
Ceramic implant placement starts from £2,000, and the ceramic implant crown starts from £1,750. Together, these start from £3,750. Extraction, bone regeneration, sinus augmentation, scans and other additional procedures are charged separately when needed.
Your written estimate will confirm the planned treatment and cost after examination. See our dental fees.