


Reviewed by Dr Nico Kamosi, last updated October 2026.
Dr Nico Kamosi provides specialist consultation, examination, treatment and Supportive Periodontal Treatment for the following conditions.
- Your clinician: Dr Nico Kamosi, a periodontist since 2000; previous senior clinical teacher in periodontology at King’s College London and Implantology at ACTA University Amsterdam.
- Conditions treated: Gum disease, gum recession and peri-implantitis, Amalgam tattoo, Gum pigmentation, Gummy smile, Smile design, Guided Tissue Regeneration (GTR)
- Consultation: Periodontal consultation, specialist investigation and report from £250.
- Appointments: Book directly or attend following a referral from your dentist.
- Location: Knightsbridge, London.
What is periodontitis?
Gum disease (periodontitis) refers to an infection-induced inflammatory process involving tooth-supporting structures.
Approximately 5% to 20% of any population suffers from severe generalised periodontitis, even though moderate periodontal disease affects a majority of adults. This most common human oral disease is caused by certain bacteria which start to increase in number and virulence when the related risk factors, such as multiplying bacterial deposits, can grow undisturbed in the unreachable gum pockets while producing by-products which may stimulate the body’s defensive inflammatory response around the teeth. This chronic inflammatory disease may progress and cause gradual bone destruction and gum recession over the years when not treated efficiently by a Periodontal specialist.
Meet your periodontist
Dr. Nico Kamosi

Dr. Nico Kamosi
Specialist periodontist, with extensive postgraduate training and experience in implant dentistry and prosthodontics; holistic and biological dentistry.
TDL. DDS. (Swe.), MSc.Perio.(Eng.),
MClinDent.Perio.(Eng.), MSc.Imp.Dent.(Eng.),
Dip.Aesth.Med. (Eng.), MClinDent.Prosth.(Eng.),
Cert., Dip.DHSLM.(RCS.Eng.), Cert.Orth.(Eng.), Cert.Law (Eng.), AIAOMT
Accredited member of IAOMT, SMART Certified
Member of AACD, EFP, AAP, ESCI, IAOMT
Dr Nico qualified as a DDS in Sweden in 1995. His qualifications include an MSc and MClinDent in Periodontology, an MSc in Implant Dentistry (UCL, 2001), and an MClinDent in Prosthodontics (King’s College London). He is one of only five IAOMT-accredited members in the UK, and SMART certified. He is a member of AACD, EFP, AAP and ESCI.
I am on the General Dental Council (GDC) Specialist List for Periodontology. My GDC registration number is 70429.
I completed my specialist training in Periodontology in 2000 and have been involved in periodontal practice for more than two decades. The number of periodontal patients I see varies considerably depending on the type of patients I visit and their specific treatment needs.
During periods when I have been teaching at university and treating predominantly periodontal patients, I have seen approximately seven to 15 periodontal patients per day. At other times, when working predominantly in my private clinic, the number of patients seen specifically for periodontal disease is lower because my clinical work also encompasses implantology, prosthodontics, restorative dentistry and multidisciplinary treatment.
I have been involved in teaching Periodontology and Implantology at King’s College and have taught and treated periodontal disease for approximately six to seven years in that setting. I have also taught at the University of Amsterdam, where I have worked as a senior supervisor in both Implantology and Periodontology.
How can the progression of periodontitis be recognised?
The inflamed, swollen gum called gingivitis may be recognised during brushing when bleeding. In some individuals, gingivitis may progress to gum disease (periodontitis) when untreated. Consequently, over time, the affected patient may experience increased gum bleeding, bad breath, drifting teeth, gum recession, and tenderness in the gum. Controversially, bleeding from the gums may be less noticeable in smokers, as nicotine has an adverse vasoconstrictive effect on blood vessels by decreasing the local blood circulation, hence reducing bleeding from diseased gums. As periodontitis is usually pain-free, it can be left unrecognised until its very progressed stages. Therefore, to treat periodontitis at the very early stage of my diagnosis, it is paramount that dental clinicians, in particular the gum specialist or periodontist, investigate the specific clinical signs and symptoms and radiographic features of gum disease at an early stage of its progressive destruction.
When to see a periodontist
Specialist assessment may be appropriate when gum disease persists despite treatment from your dentist or hygienist.
If a patient has been receiving treatment for gum disease from their dentist for an extended period and the periodontal condition has not been successfully controlled, I would recommend assessment by a periodontist. Similarly, if a patient has been under the care of an oral hygienist for a prolonged period but there has been little or no improvement, or if there are persistent periodontal sites that are not responding adequately to conventional treatment, specialist periodontal assessment is appropriate.
Early specialist assessment can be particularly important where there is:
- Persistent bleeding
- Deep periodontal pockets
- Progressive bone loss
- Tooth mobility
- Furcation involvement
- Gum recession
- Recurrent periodontal inflammation or infection
- Persistent disease despite good oral hygiene
- Suspected need for periodontal regeneration or periodontal surgery
You can book directly or ask your dentist to refer you. Read more about when to see a periodontist rather than a general dentist.
When a patient is referred by another dentist or healthcare professional, I undertake the same comprehensive periodontal assessment and treatment-planning process. Once the periodontal treatment has been completed, I provide a report to the referring dentist outlining the periodontal findings, treatment undertaken and recommendations for ongoing care.
The referring dentist can then continue with the patient’s general and restorative dental care, while I continue to provide specialist periodontal treatment, monitoring and supportive periodontal therapy where required. This allows the patient to benefit from a multidisciplinary approach, with the general dentist and periodontist working together.
Causes of Periodontitis
Retention or accumulation of dental plaque around the teeth may gradually enhance the number and virulence of the bacterial colonies, which may, in turn, reduce the natural defence system of the local tissue. The salivary minerals and gingival crevicular fluid may gradually cause sedimentation of growing bacterial plaque and the creation of harder deposits called tartar or dental calculus. This bacterial growth is further facilitated along the root surfaces, causing an inflammatory process which destroys the peripheral periodontal tissues via the gum pockets. This bacterial infection-induced inflammatory process, which causes progressive destruction of the tooth-supporting/periodontal tissues, is called periodontitis.
The pathologic pocket around the root surface favours the colonisation, growth and multiplication of the virulent bacteria, which are capable of destroying the tissues both directly by releasing destructive enzymes, toxins and other by-products which compromise the body’s defence mechanisms and indirectly by inflammatory stimulation of the local immune system.
Read more about the diagnosis and treatment of periodontal disease.
Prevention of Periodontal Disease
The risk factors involved in the emergence and progression of periodontitis could be divided into the local virulent factors, e.g., the number and type of virulent bacteria; the host factors, such as the ability of the individual’s local and systemic defence mechanisms coupled with the tissue healing capacity; the presence of confounding risk factors which compromise the host response, e.g. smoking, certain drugs regulating the tissue response, as well as inherent immune-suppressive factors such as stress systematic disease. Factors prevailing in chronic gingivitis should be recognised and addressed during professional dental and periodontal examinations and treatment sessions.
It is scientifically well-proven that smoking adversely affects the status of local health, healing, and immune response of periodontal tissues and the successful treatment of gum disease as a result.
Is periodontitis correlated to other systemic chronic inflammatory diseases?
Based on the case studies, clinical research, and epidemiological studies, there are strong evidence-based associations between chronic gum infection or periodontal disease and cardiovascular disease (CVD), Alzheimer’s disease, erectile dysfunction syndrome, low-weight child disease, and premature parturition. Read more on the correlation between periodontal disease and other systemic inflammatory diseases, e.g., cardiovascular diseases.
In patients with diabetes, there is a well-established two-way relationship between periodontal disease and glycaemic control. Periodontal inflammation can be associated with poorer glycaemic control, while poorly controlled diabetes can increase the risk and severity of periodontal disease.
Clinical research has also demonstrated that successful periodontal treatment can be associated with improvements in measures of glycaemic control, particularly in patients with type 2 diabetes, although periodontal treatment should not be regarded as a replacement for appropriate medical management of diabetes. There is also an established association between periodontal disease and cardiovascular disease and cardiovascular risk factors. However, it is important to distinguish an association from proof that periodontal disease directly causes cardiovascular disease.
Read more about diabetes, hormonal changes and gum disease.
Your periodontal treatment pathway
Treatment begins with a comprehensive periodontal tissue assessment, followed by an initial phase of cause-related non-surgical treatment of the disease, re-evaluation and supportive Periodontal maintenance.
Assessment
The first appointment involves a comprehensive clinical and periodontal assessment.
This includes:
- Full-mouth periodontal charting
- Six-point periodontal pocket charting
- Plaque score
- Bleeding score and bleeding on probing
- Furcation involvement
- Tooth mobility
- Clinical attachment loss
- Gingival recession
- Periodontal pocket depths
- General oral health assessment
- Medical history and general health assessment
- Previous history of periodontal disease
- Family history of gum disease
- Social history and relevant lifestyle habits
Radiographic assessment is also undertaken where clinically indicated. Depending on the extent and severity of the disease, this may involve an OPG, intraoral periapical radiographs or CBCT imaging.
Initial phase of treatment
The next stage is the cause-related initial phase of periodontal treatment.
This includes:
- Oral hygiene instruction
- Explanation of periodontal disease and its contributing factors
- Dietary advice where appropriate
- Smoking cessation advice
- Brushing instruction
- Interdental cleaning instruction
- Motivation and patient cooperation
- Supragingival debridement
- Full-mouth debridement where appropriate
- Subgingival periodontal instrumentation under local anaesthesia where required
The objective is to control bacterial biofilm and the local factors contributing to periodontal inflammation. EMS Guided Biofilm Therapy and laser-assisted procedures may be incorporated where clinically appropriate, both during non-surgical and surgical periodontal treatment.
Regenerative periodontal treatment
Not every periodontal defect has the same regenerative potential. Where there is limited potential for regeneration, conventional non-surgical periodontal treatment may be the appropriate approach.
Where there is a suitable periodontal defect with potential for periodontal regeneration and reattachment, Emdogain may be considered as part of a regenerative periodontal treatment approach. Where there is greater potential for bone regeneration and reconstruction, L-PRF may be used together with appropriate bone-grafting materials, as part of a regenerative or guided tissue regeneration approach where clinically indicated. The choice of treatment is determined by the individual periodontal defect, the remaining bone and periodontal attachment, the patient’s general health, risk factors and ability to maintain appropriate oral hygiene and cooperate with treatment.
Read about periodontal regeneration.
Re-evaluation
Regenerative treatment is not normally undertaken immediately without first addressing the underlying causes of periodontal disease. Following completion of the initial phase of cause-related treatment, the patient is generally reassessed after approximately three to four months. At this stage, we assess the periodontal response to treatment.
If remaining periodontal pockets are amenable to further conventional non-surgical periodontal treatment, the initial treatment may be repeated or further periodontal instrumentation undertaken. If there are residual periodontal defects with potential for periodontal or bone regeneration, the appropriate regenerative options can then be discussed with the patient.
Supportive periodontal treatment
Once active periodontal treatment has been completed, the patient does not simply disappear from care. Periodontal disease is a chronic condition with a risk of recurrence or progression, and supportive periodontal therapy (SPT) is an essential part of long-term periodontal management.
I generally recommend quarterly periodontal evaluation and supportive periodontal treatment during the first year, followed by approximately six-monthly maintenance during the second year and thereafter, depending on the individual patient’s periodontal status and risk profile. The exact recall interval is individualised according to the patient’s periodontal condition, risk factors, oral hygiene, smoking status, systemic health and response to treatment.
Treatment of Periodontitis
With careful assessment and treatment, it is usually possible to completely halt the progress of periodontitis. The key to success is to eliminate the bacterial plaque triggering the periodontal disease process and establish excellent oral hygiene practices.
At London Specialist Dentist, we provide the following periodontal specialist services:
• Clinical assessment, diagnosis, and treatment of the patient with aggressive and chronic periodontitis.
• Diagnosis and treatment planning for patients with the oral manifestation of systemic disease.
• Clinical assessment, diagnosis, and treatment of patients who require post/endodontic and/or pre-prosthodontic root amputation and crown lengthening.
• Clinical assessment, diagnosis, and treatment of young patients who require pre-orthodontic surgical tooth exposure and patients who require post-orthodontic surgical soft tissue and hard tissue regenerative procedures.
• Clinical assessment, diagnosis, and treatment of patients with clinical periodontal disease symptoms in need of occlusal re-organisation by means of fixed and removable prosthodontics.
• Clinical assessment, diagnosis, and treatment of patients presenting with peri-implantitis.
At London Specialist Dentist, we implement triple-wavelength technology in dentistry using the latest generation of lasers. The Laser Infrared wavelength is effectively used in the decontamination of infected periodontal and peri-implant pockets, and infected root canals as an adjunct to the mechanical and chemical debridement within the periodontal, peri-implant and Endodontic treatment protocols. This means the indication for adjunct use of antibiotics and their consequent side effects is drastically reduced.
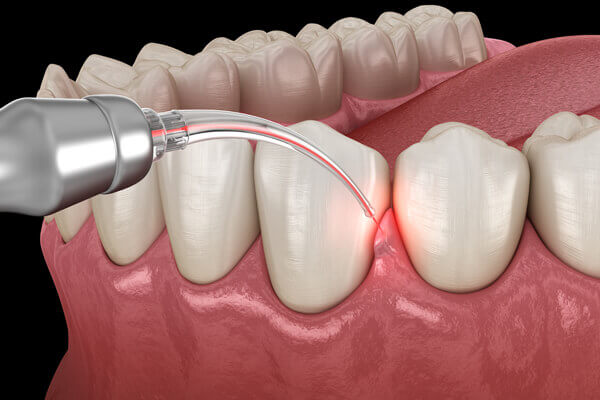
We implement the innovative technology of laser-assisted periodontal therapy (LAPT) to improve periodontal health with minimal discomfort following both non-surgical and surgical periodontal treatment interventions. During endodontic treatment, LASER is utilised after preparing and rinsing the root canal in addition to the conventional treatment.
Learn more about periodontal laser and ozone therapy and peri-implantitis assessment and treatment.
Our periodontal prevention treatment services:
We can help to prevent periodontal diseases with a comprehensive range of treatments personalised to the needs of each patient. Here are some key periodontal treatments you can expect to find at our practice:
- Scaling and Root Planing: A deep cleaning procedure to remove plaque and tartar from below the gum line, preventing the progression of gum disease.
- Pocket Reduction Surgery: Surgical procedures to eliminate pockets and reduce the space between the teeth and gums, facilitating better hygiene.
- Gum Grafting: Restoring receding gums by grafting healthy tissue from one area to another.
- Dental Implants: Replacing missing teeth due to severe gum disease with stable, long-lasting dental implants such as a ceramic zirconia implant.
- Bone Grafting: Augmenting the jawbone to support dental implants or improve the structural integrity of teeth.
- Ongoing Maintenance: Regular check-ups and cleanings with a dental hygienist to manage and prevent recurrence of gum disease.
How is gum recession treated?
Traumatic brush damage is a common clinical presentation in adults, especially in women after the age of 40. Composite filling restorations are often advocated by some dentists, which may at times worsen the situation and eventually cause more recession. However, a gingival or gum transplant replaces the retreated gum while addressing tooth hypersensitivity and aesthetically disturbing root exposure.
Explore gum recession treatment and our gum transplant case studies.
Gum depigmentation treatment
Excessive melanin can be caused by a reaction to local invasive thermal or toxic chemical trauma, e.g., smoking and certain types of medications, leading to discolouration and hyperpigmentation of the gum, hence aesthetically disturbing the gum for some individuals.
Melanocytes are melanin-producing cells that could be targeted by the LASER treatment, which dramatically reduces melanocyte activity, hence melanin synthesis. The gingival depigmentation or gum bleaching procedure is usually a quick and painless procedure.
Read more about gum depigmentation.
Online Periodontal Self Assessment
Online Periodontal Self AssessmentPeriodontology Case Studies
See our periodontology before-and-after photos from our happy patients.
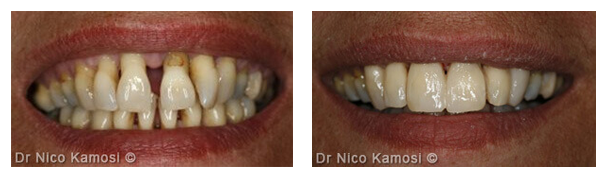
Before and After Treatment
Treated advanced generalised periodontitis followed by restorative correction of the advanced gum recession.
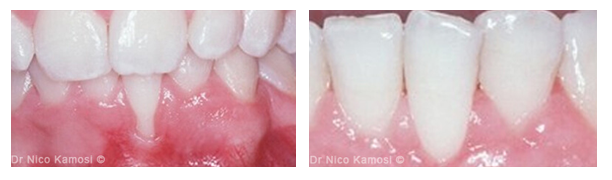
Before and After Treatment
Thin periodontal biotype, gingival recession, reduced vestibular depth, aberrant frenum/muscle pull, exposed root surface.
What results can you expect?
The response to periodontal treatment depends on your condition, healing capacity and ongoing care.
The patient’s expectations should always be based on their individual clinical circumstances and biological capacity to heal. Every patient is different. Each person has their own genetic disposition, general health, medical history, healing capacity, diet, lifestyle and oral-health habits. These factors can all influence the extent and quality of healing.
Therefore, periodontal treatment is always case-specific, and no clinician can guarantee an identical biological response in every patient. The patient’s cooperation is also extremely important. Oral hygiene, smoking, diet, attendance, maintenance and adherence to treatment recommendations can all influence the outcome.
When is a tooth no longer worth saving?
A tooth may be considered non-salvageable or to have an unfavourable or hopeless prognosis when there is extensive loss of supporting bone, extensive infection, significant loss of tooth structure or another condition that means the tooth cannot be predictably repaired, maintained or retained.
Examples may include:
- Extensive periodontal bone loss
- Severe periodontal infection
- Severe loss of periodontal support
- Extensive loss of tooth substance
- An unresolved periapical infection following previous root canal treatment
- A fractured or broken tooth that cannot be predictably restored
- A combination of periodontal, endodontic and restorative problems that makes long-term retention unpredictable
In these circumstances, I discuss the prognosis openly with the patient and explain the available treatment options, including whether there is a realistic possibility of retaining the natural tooth or whether removal and subsequent replacement should be considered.
Periodontal treatment fees
A periodontal consultation, specialist investigation and report starts from £250.
| Treatment | Fee |
|---|---|
| Periodontal consultation, specialist investigation and report | From £250 |
| Hygienist treatment by dentist | From £200 |
| Advanced hygienist treatment including Air-Flow | From £250 |
| Regenerative non-surgical periodontal treatment, per quadrant | From £800 |
| Regenerative surgical periodontal treatment, per quadrant | From £1,200 |
| Correction of gum recession | From £1,000 |
| Gum recession correction, tunnel technique with tissue regeneration | From £1,600 |
| CBCT scan | From £150 |
| CBCT report | From £100 |
Your final cost will be confirmed after examination and provided in a written estimate. See our dental fees.
Find our Knightsbridge clinic
Our clinic is on Brompton Road in Knightsbridge.
Address: Unit A, 4th Floor, 193-195 Brompton Road, Knightsbridge, London SW3 1NE
Nearest Tube: Knightsbridge (Piccadilly line)
Phone: 020 7207 5222
Patients travelling from Kensington, Chelsea and Central London can plan their journey to the Brompton Road address or Knightsbridge station.
Questions about periodontal care
Your assessment will establish which treatment and maintenance arrangements are appropriate for you.
CVD encompasses a variety of cardiovascular pathologies, such as angina pectoris, myocardial infarction, and heart failure, as a result of inflammatory processes caused by atherosclerosis.
Atherosclerosis causes compromised blood flow to the heart and increases strain on the heart, manifesting symptoms of CVD, including intense chest pain, breathlessness, dizziness, and fatigue.
Based on the consensus report on periodontitis and cardiovascular disease (CVD), periodontal pathogenic bacteria could induce the development of atherosclerosis in the form of deposit stagnation along the inner walls of cardiac blood vessels, hence reducing vascular diameter and eventually causing vascular occlusion.
Atherosclerosis causes a compromised natural blood flow to the brain. A temporary disruption of the brain blood supply may lead to a transient ischaemic attack and, when prolonged, to stroke.
If you have any concerns about the health of your gums or potential periodontal issues, it’s essential to schedule an appointment with a qualified periodontist and gum specialist.
Patients are often surprised that their gums can continue to bleed despite good brushing. Bleeding is an important clinical sign of gingival or periodontal inflammation and should not simply be ignored.
Patients understandably want to know what treatment will involve and whether they will experience discomfort. Local anaesthesia and modern periodontal techniques allow treatment to be carried out comfortably in most cases.
There is no single answer. The duration depends on the severity and extent of periodontal disease, the patient’s response to treatment, the need for regenerative or surgical treatment, and the patient’s cooperation. In some patients, treatment may take many months or, where a comprehensive multidisciplinary or regenerative approach is required, approximately a year or longer.
Importantly, completion of active periodontal treatment does not mean that the patient no longer requires care. Once a patient has developed periodontal disease, there remains a risk of recurrence or progression. Long-term supportive periodontal therapy is therefore an essential part of maintaining periodontal health.
Yes. Patients can book a periodontal consultation directly. They can also be referred by their dentist, another healthcare professional or, where appropriate, a doctor or functional medicine practitioner.
A periodontal consultation, including specialist examination and report, starts from £250. Regenerative non-surgical periodontal treatment starts from £800 per quadrant, and regenerative surgical periodontal treatment starts from £1,200 per quadrant.
The cost depends on the number of treatment sessions required and the type and extent of periodontal treatment undertaken. A precise estimate can therefore only be provided following an appropriate clinical assessment and treatment plan.